

Talking to yourself is a natural and very common behavior among healthy people, and doesn’t in itself mean madness or mental illness. A person talks to themselves in a low voice while looking for their keys, encourages themselves before an interview, or rearranges their day in the shower. But in fewer cases, talking “with someone who isn’t there” may be a sign of auditory hallucination or confusion that needs an assessment.
The difference between the two cases isn’t whether there is talking, but who is speaking and who is answering, how much it troubles the person, and how it affects their life. Here we explain healthy inner speech, when it helps, the signs of talk that deserves attention, how to tell them apart, and how to improve your inner dialogue if it is harsh. Diagnosis comes from a specialist, not an article.
Why do we talk to ourselves at all?
Language isn’t only a way of communicating with others, but a tool for thinking. Young children talk out loud as they play and solve problems, then over time this talk turns into a silent inner voice for most adults, which reappears out loud when a person faces a difficult task or pressure. Psychological studies suggest that talking to oneself may help with concentration, organizing steps, remembering things and controlling emotions, which is why athletes, students and people doing precise work use it. And in this case the person knows they are the one speaking, and can stop whenever they want.
Forms of normal self-talk
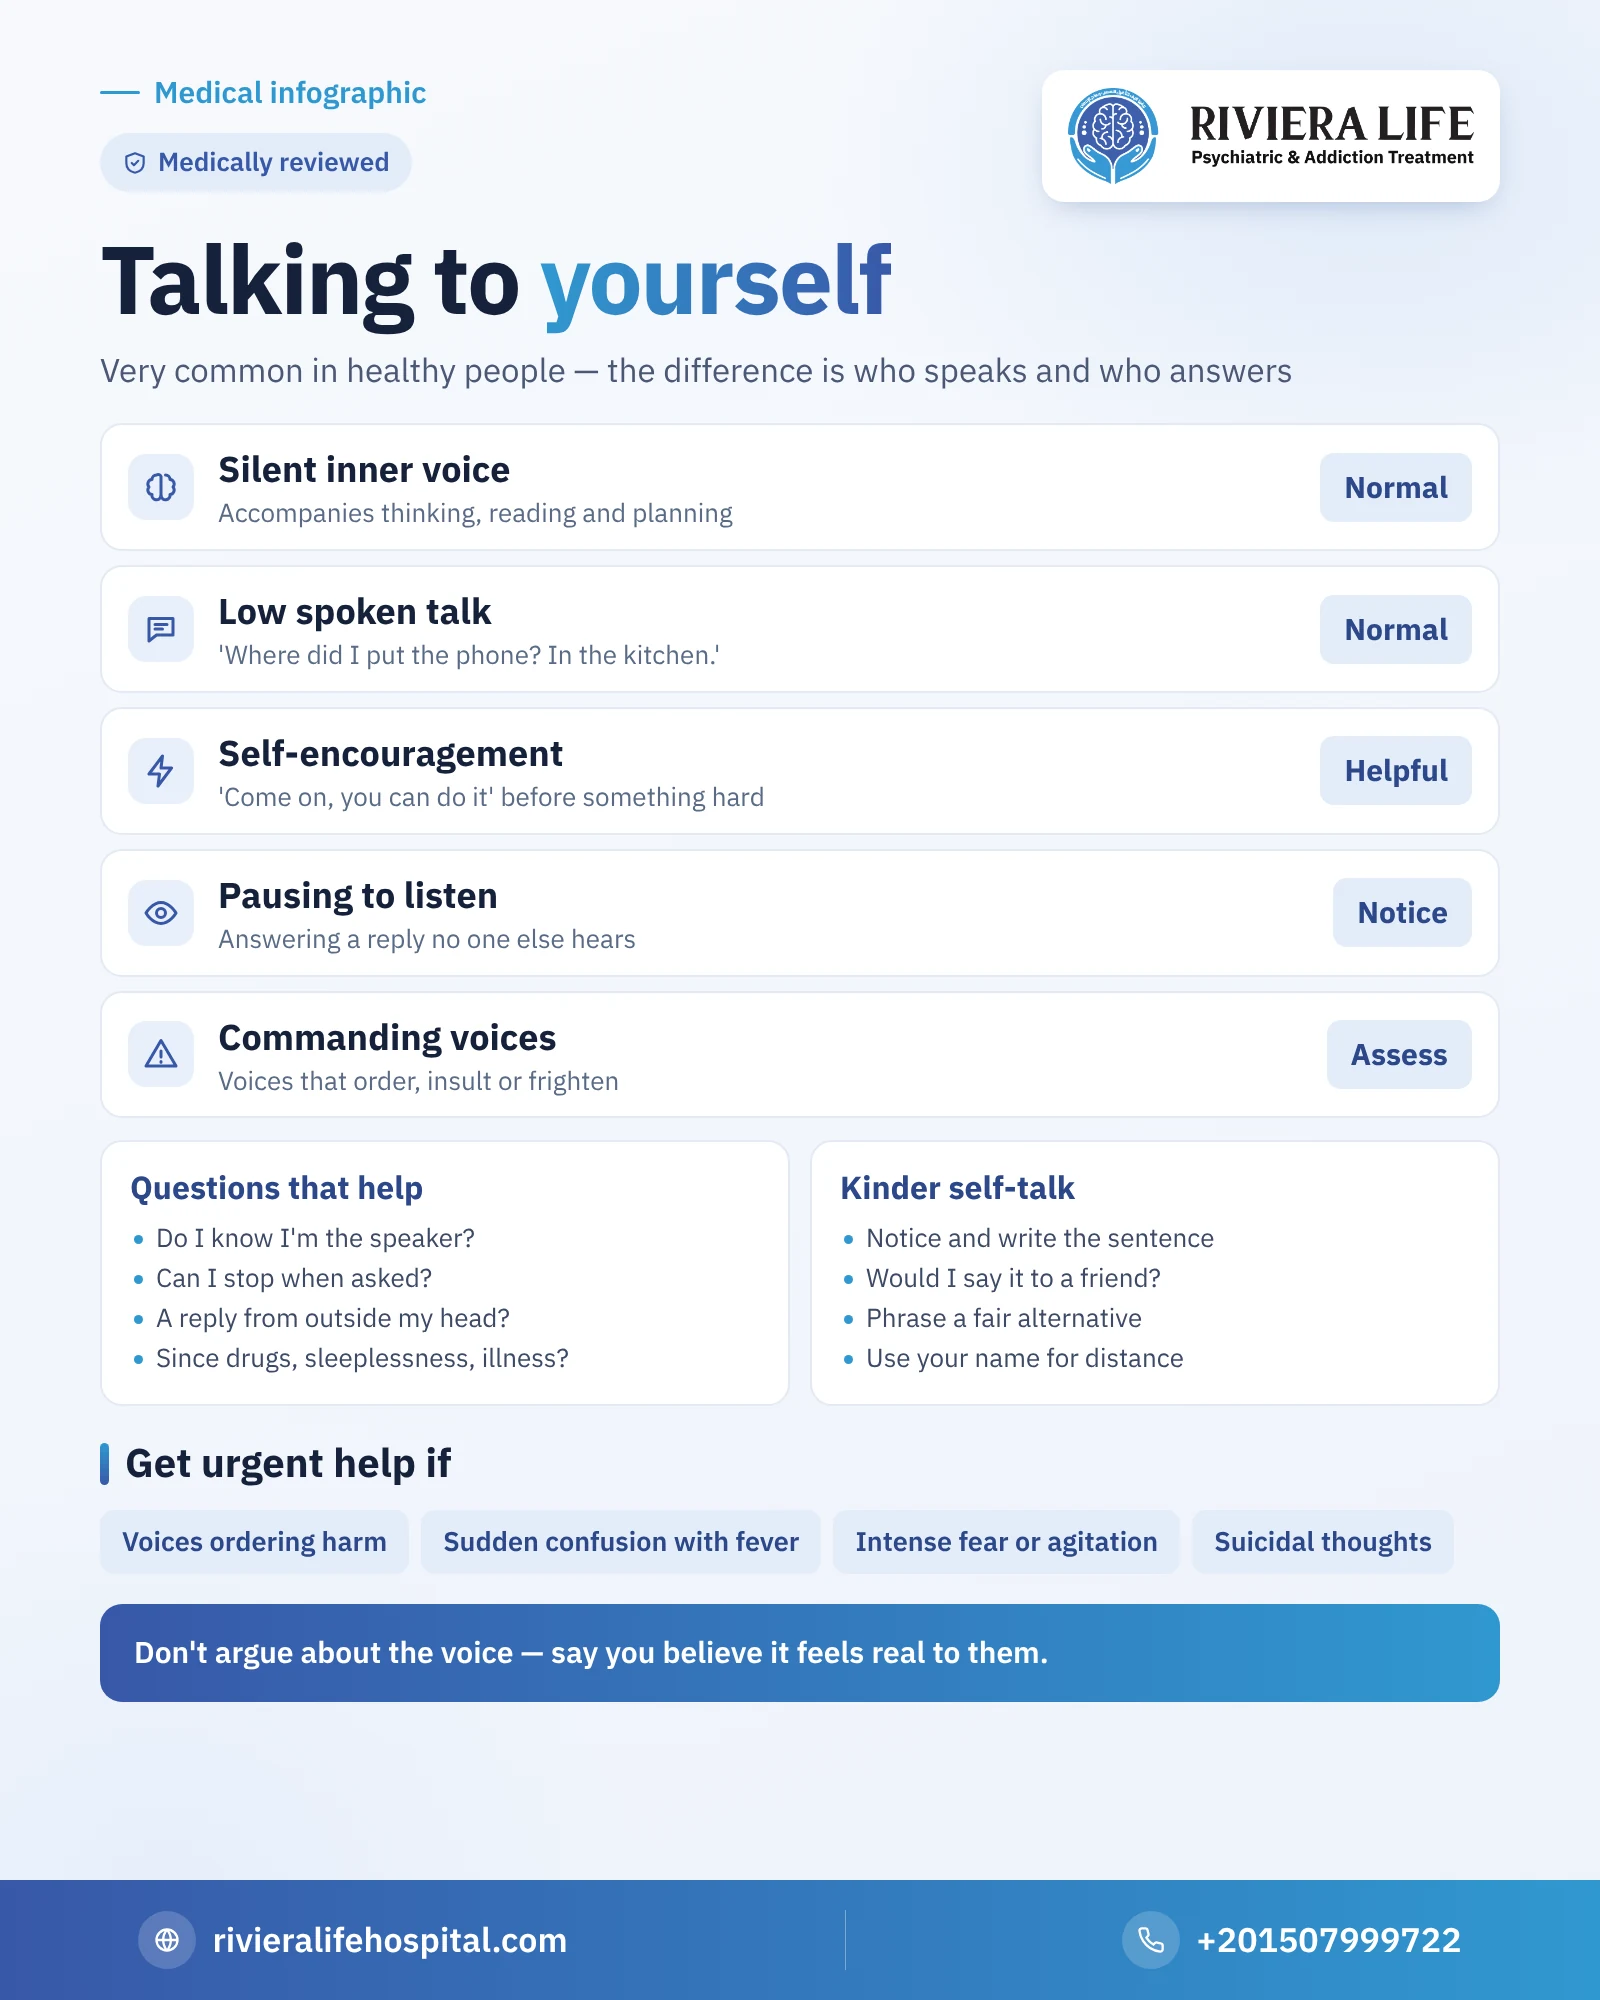
- Silent talk: the voice that accompanies thinking, reading and planning inside the head.
- Low spoken talk: “Where did I put the phone? In the kitchen.”
- Encouragement and motivation: “Come on, you can do it” before something difficult.
- Blame or grumbling: “How did I forget this!” after a mistake.
- Rehearsing a conversation: replaying a conversation with a manager or partner before or after it happens.
- Addressing someone we have lost: many bereaved people talk to the one who has gone, a common part of grief that isn’t considered illness, as long as the person is aware they are no longer there.
When does it become different?
It deserves attention when the talk turns from a dialogue with oneself into a dialogue with another person or voice that the person hears and others don’t. In this case the following signs recur:
- The person talks, then stops as if listening, and responds to an answer those around them don’t hear.
- They say someone is whispering, commenting on their actions, ordering them or insulting them.
- They show fear, anger or laughter for no understandable reason while talking.
- The tone of voice changes as if exchanging dialogue between two different parties.
- The speech is disjointed and unconnected to what is around them, or repeats without stopping.
- It is accompanied by long sleeplessness, isolation, suspicion of those around them, or neglect of hygiene.
- They can’t stop, or feel it is beyond their will.
These signs are what doctors call auditory hallucinations, and we explain their types in types of hallucination and what the family notices in hallucination symptoms.
Simple questions that help you tell the difference
You can ask yourself or your relative these questions calmly and without accusation:
- Do I know that I am the one speaking?
- Can I stop talking if I’m asked to?
- Does a reply come to me in a voice that seems to be from outside my head or from another person?
- Does the voice order me to do something, frighten me or insult me?
- Have I started avoiding people, sleeping less, or has my work declined because of it?
- Did it begin after a drug, long sleeplessness, a shock or a physical illness?
The answers don’t diagnose, but they show whether reassurance is enough or a visit to the doctor is needed. The more “yes” answers to the last questions, the greater the need for an assessment.
What may lie behind worrying talk?
Talking with someone who isn’t there isn’t a single illness, but a sign that may appear in several conditions:
- Psychotic disorders: such as schizophrenia and brief psychotic disorder, and some other forms of psychosis.
- Severe depression or mania: these may sometimes be accompanied by voices that match the mood.
- Drugs and alcohol and their withdrawal: especially stimulants, hashish and hallucinogens, which is the subject of drug-induced psychosis.
- Delirium: a sudden confusion of consciousness due to infection, medicines or a physical disturbance, especially in older people, which is an urgent medical condition.
- Dementia: in older people, the patient may talk to people from the past or to their reflection in the mirror.
- Severe sleep deprivation and trauma: these may cause temporary auditory experiences.
- Hearing a voice on falling asleep or waking: a brief experience common in healthy people that usually doesn’t mean illness.
Harsh negative self-talk
Not every worrying talk is about voices. Sometimes the problem lies in the content of the inner dialogue: “I’m a failure”, “nobody loves me”, “I’ll get it wrong as usual”. This type is linked to anxiety, depression and low self-esteem, and feeds on itself. Research shows that negative automatic thoughts can be modified with practice. This doesn’t mean repeating artificial positive phrases, but treating thoughts as thoughts rather than facts.
- Notice the sentence you said to yourself and write it down.
- Ask: would I say it to a friend in my place? And what is the evidence for and against it?
- Phrase a fairer alternative: “I got this wrong, and I’ll fix it” instead of “I’m a failure”.
- Address yourself in the third person or by your name sometimes, as this gives you a distance that helps you calm down.
- If dark thoughts stay with you for weeks, ask for an assessment, as they may be a sign of depression.
What should you do if you notice this in a relative?
- Don’t mock them or call them mad, and don’t interrupt them sharply.
- Ask calmly: do you hear something? What is it saying to you? Does it frighten you?
- Don’t argue about whether the voice exists; say: I don’t hear it, but I believe it is real for you.
- Record when it began and how often it happens, and whether it was preceded by sleeplessness, drug use or pressure.
- Suggest seeing a psychiatrist, and if it is sudden with confusion or fever, go to the emergency department.
Seek urgent help immediately if you see
Call an ambulance on 123 or go to the nearest emergency department.
- Voices ordering harm to oneself or others
- Sudden confusion and not knowing the place or time, with fever
- Intense fear, agitation or trying to run away
- Refusing food and water, or suicidal thoughts
You can also ask for guidance from the hotline of the General Secretariat of Mental Health on 16328.
How does the doctor assess the case?
The doctor listens to a detailed description of the experience: what the person hears, when it began, and whether they understand it as a voice from inside or outside themselves. Then they ask about sleep, drugs, medicines and mood, check the physical side with tests when needed, and meet a family member. If it turns out to be just normal inner speech, reassurance may be the treatment. If hallucinations appear, the plan is built on the cause, as we explain in hallucination treatment, and when do you need a psychiatrist offers guidance on the first visit.
Common ideas and their correction
- “Someone who talks to themselves is mad”: untrue; it is a common behavior among healthy people and helps in many situations.
- “Voices are evidence of weak faith or magic”: no; hallucinations are medical symptoms with causes and treatment.
- “Hearing a voice once means illness”: not necessarily; brief experiences on falling asleep or when exhausted can happen to healthy people.
- “Treatment is useless”: many patients improve with the right treatment.
How can Riviera Life help you?
At Riviera Life, consultants in psychiatry and addiction listen to the experience without judgment, distinguish between normal talk and hallucinations and their causes, and set a treatment plan, a family program and aftercare in complete confidentiality. The first consultation is free, and you can get in touch around the clock on +201507999722.
More from our psychosis guide
Questions many people ask
No, it is very common among healthy people and helps with concentration and organizing thoughts; what matters is who is speaking, who is answering, and how much it affects life.
In normal talk, the person knows they are the speaker and stops when they wish, whereas in hallucination they hear a voice from outside their head and answer it.
Many bereaved people do it, and it is a common part of grief, as long as they are aware the person is gone and carry on with their lives.
When you hear voices that order, insult or frighten, or if the talking comes with sleeplessness, isolation, suspicion or a decline in functioning.
Yes, by noticing the sentence, examining its evidence and phrasing a fair alternative, and with cognitive behavioral therapy if it persists or is linked to depression and anxiety.


